Nose Surgery
Rhinoplasty in Melbourne
Dr Rodrigo Teixeira FRACS, Specialist Plastic Surgeon
Rhinoplasty is tailored nasal surgery that may address cosmetic concerns, structural support and breathing-related issues. Primary rhinoplasty is planned with careful attention to facial balance, nasal anatomy, function and long-term stability as healing progresses, as part of a practice focused on facial plastic surgery in Melbourne.
Suitability
Why rhinoplasty may be considered
Rhinoplasty, sometimes referred to as a nose job, nose surgery or nose reshaping, may be considered to change the shape, proportion, or contour of the nose. It may address aesthetic concerns, breathing-related concerns, or both.
Planning does not focus on one feature alone. The bridge, tip, septum, internal valves, skin thickness, structural support, and facial proportions all influence what may be appropriate and what may be achievable.
Breathing concerns may relate to structural factors such as septal deviation, weakness in nasal support, or narrowing of the nasal valves. Previous injury or trauma may also affect both appearance and airflow and may influence the surgical plan.
A consultation is required to assess suitability, discuss limitations, and determine whether rhinoplasty is the most appropriate option.

Techniques
Types of rhinoplasty surgery
Cosmetic rhinoplasty – nose reshaping surgery
Cosmetic rhinoplasty planning focuses on the appearance of the nose and how it sits in balance with the rest of the face. This may include assessment of nasal shape, bridge contour, tip definition and support, skin characteristics, and overall facial proportions. For patients whose main concern is aesthetic, the surgical plan is tailored to their anatomy, goals, and what is appropriate for their features.
Functional rhinoplasty – nasal airway surgery
Functional rhinoplasty planning focuses on breathing and the structural support of the nose. This may include assessment of the nasal airway, internal support, septal alignment, and other factors that may affect airflow or nasal function. Where appropriate, functional concerns are considered alongside appearance to develop a surgical plan tailored to the individual.
Revision rhinoplasty
Revision rhinoplasty is performed to address concerns following a previous nose operation. This may involve changes to nasal shape, support, asymmetry, scarring, or breathing, depending on the individual. Planning considers the existing anatomy, prior surgical changes, and what can be improved safely and realistically.
What concerns may rhinoplasty address?
Rhinoplasty may be considered for concerns related to nasal shape, balance, structure, or breathing. In many cases, what appears to be a single visible concern reflects deeper anatomy, which is why assessment looks beyond one feature alone.
Common concerns may include:
- a dorsal hump, bridge prominence, or bump on the nose
- tip droop, reduced projection, or limited definition
- a nose that feels too large, prominent, or out of balance with other facial features
- a crooked or deviated appearance
- asymmetry
- nostril flare or width
- a wide bridge or broad nasal shape
- changes after injury
- structural concerns affecting airflow
- breathing difficulty related to nasal structure
Not every concern is best managed with surgery, and not every patient will be a suitable candidate. This is discussed carefully during consultation.
Suitability
Who may be suitable for rhinoplasty
Rhinoplasty may be an option for adults, and for older teenagers whose nasal growth is complete, who have a specific concern about the shape, symmetry or function of the nose and are in good general health. Skin thickness, cartilage strength and any previous treatment all influence what can be achieved, so suitability is always assessed individually.
Factors that support a good outcome include:
- a clear, specific concern rather than a general wish for change
- realistic expectations about what surgery can and cannot alter
- good general health and no active nasal infection
- not smoking, or being willing to stop, as smoking impairs healing
- a willingness to follow aftercare and attend review appointments
Where nasal filler has been used previously, it may need to be dissolved and allowed to settle before surgical planning so that the underlying anatomy can be assessed accurately. Patients who have had earlier nose surgery are assessed for revision rhinoplasty, which is planned separately. Where expectations and the likely surgical result do not align, surgery may not be recommended.
How is rhinoplasty assessed and planned?
Rhinoplasty begins with assessment of both nasal appearance and function. Visible concerns may reflect deeper anatomy, so planning considers more than one feature in isolation. Patients considering rhinoplasty in Melbourne are assessed with attention to nasal shape, support, breathing, and overall facial balance.
Assessment may include nasal shape, bridge contour, tip support, breathing, skin characteristics, alignment, and how the nose sits in balance with the rest of the face. Because nasal form and function are closely connected, cosmetic and structural factors are often considered together to guide a surgical plan tailored to the individual.
Common areas assessed in rhinoplasty planning
Bridge contour and dorsal profile
A dorsal hump may involve bone, cartilage, or a combination of both. In some patients, the concern is not only the height of the bridge, but how it relates to radix position, tip support, and overall facial balance.
Planning considers the underlying framework rather than treating the bridge as an isolated feature. Depending on the anatomy and the changes required, surgery may involve careful reshaping of the bony and cartilaginous dorsum, preservation principles in selected cases, or structural modification where greater change is needed.
Nasal tip shape, support, and definition
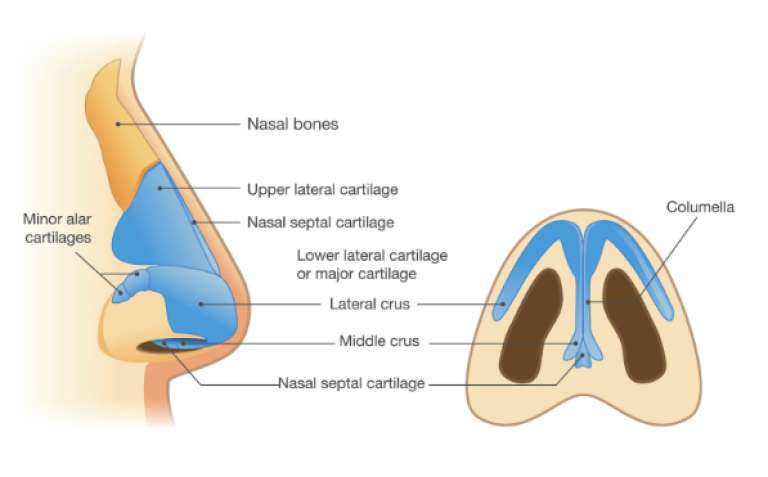
Tip concerns may include width, heaviness, asymmetry, reduced definition, or poor support. These features are influenced by the shape of the lower lateral cartilages, tip projection, rotation, skin thickness, and the strength of structural support.
Planning focuses on how the tip sits in relation to the bridge, upper lip, and other facial features. Depending on the anatomy, surgery may involve refinement, repositioning, or support of the tip framework to improve contour while maintaining stability.
Tip projection and rotation
A drooping or underprojected tip can influence both nasal appearance and facial proportions. In some patients, tip descent becomes more noticeable on smiling or in profile view. In others, limited projection may affect support and definition.
Planning considers projection, rotation, support, and the relationship between the tip and the dorsal profile. The surgical approach depends on whether the concern relates to cartilage shape, weak support, septal influence, or the balance between different parts of the nose.
Nasal alignment and deviation
A crooked or deviated nose may reflect asymmetry of the nasal bones, septal deviation, cartilage irregularity, prior trauma, or a combination of structural factors. In some patients, the concern is mainly visual. In others, it may also affect breathing.
Planning may involve straightening the bony and cartilaginous framework, while recognising that underlying asymmetry and tissue memory can influence healing. The aim is to improve alignment and balance, with discussion of any limitations that may apply.
Breathing and structural support
Some patients seek rhinoplasty because of both appearance and function. Breathing concerns may relate to septal deviation, internal or external valve narrowing, prior injury, or weakness in support.
Where airflow is affected, planning may need to address both cosmetic and functional anatomy. Depending on the findings, the surgical plan may involve septal work, structural support, or grafting where appropriate to help improve stability and airflow over time.
Previous nasal injury, nose filler, or prior surgery
Trauma, previous surgery, or prior filler may alter nasal shape, support, contour, tissue characteristics, and breathing. These situations often require more detailed assessment because scar tissue, altered anatomy, or filler-related distortion can affect both planning and what is appropriate surgically.
Where there is a history of previous treatment, consultation focuses on clarifying the underlying anatomy, identifying structural limitations, and deciding whether surgery is advisable, or whether a more specific assessment pathway may be needed.
How surgical approach is determined
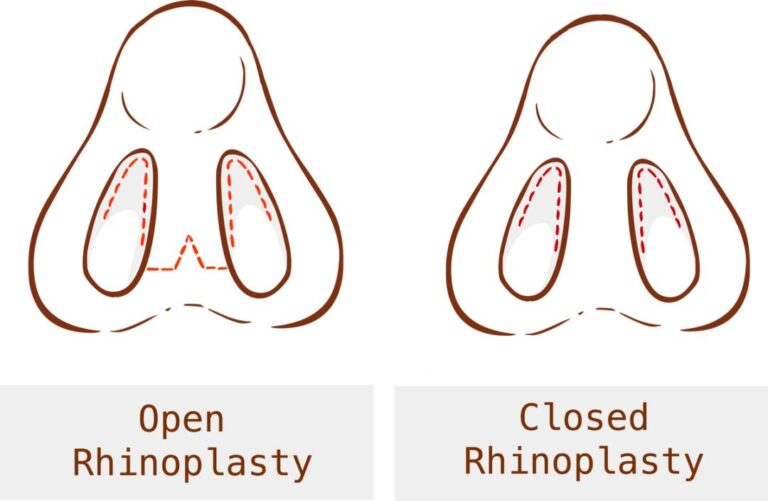
Nose surgery may be performed using different approaches depending on the anatomy, the changes required, and the level of access needed to the nasal framework. This may include open or closed rhinoplasty, as well as preservation or more structural techniques where appropriate.
An open approach may be used where direct visibility supports careful modification, structural grafting, or more detailed tip work. In selected cases, preservation principles may be incorporated to maintain key support structures and minimise unnecessary disruption. The surgical approach is determined by anatomy and planning requirements, not by a one-size-fits-all preference.
Your journey
What happens at the consultation?
The consultation is an opportunity to assess your concerns in detail and determine whether rhinoplasty may be appropriate for your anatomy and goals. This usually includes:
- discussion of cosmetic, breathing, injury-related, or previous treatment concerns
- assessment of nasal shape, structure, support, and skin characteristics
- review of facial proportions and profile balance
- breathing and structural assessment where relevant
- review of your medical history and prior treatment history
- discussion of suitability, risks, recovery, limitations, and next steps
You’ll have time to explain what is bothering you, whether the concern relates to appearance, breathing, past injury, or a combination of factors.
The consultation includes assessment of nasal shape, structure, support, skin characteristics, and how the nose relates to the rest of the face. Where helpful, clinical photography and optional imaging may be used to support communication during planning. These tools can help clarify priorities, but they do not predict exact outcomes.
The discussion also covers what may be achievable, what may be limited, likely recovery, risks, and whether surgery is the most appropriate option.

Informed consent
Risks and considerations
Like all surgical procedures, rhinoplasty carries risks and potential complications. These vary depending on anatomy, medical history, tissue characteristics, healing response, and the extent of surgery performed. Because healing cannot be fully predicted, both aesthetic and functional outcomes may change over time, and specific results cannot be guaranteed.
Risks and considerations discussed during consultation may include:
- bleeding, infection, scarring, and anaesthetic risks
- contour irregularities or residual asymmetry
- recurrence of deviation
- internal scarring that may affect airflow
- graft-related healing issues where grafts are used
- temporary or prolonged changes in sensation
- persistent breathing concerns or structural healing issues
- the possibility that further treatment may sometimes be considered after healing
All procedures carry risks. A consultation is required to assess suitability and discuss these in the context of your individual anatomy and surgical plan.
Your journey
The day of surgery
Rhinoplasty is performed under general anaesthetic in an accredited private hospital, with a specialist anaesthetist. The operation usually takes two to four hours, depending on whether the surgery is limited to the tip or bridge or involves more extensive structural work, septal surgery or grafting.
Whether you go home the same day or stay one night depends on the extent of surgery, whether it is combined with another procedure and what is most comfortable for you. This is decided with you during planning. You will need someone to take you home and stay with you on the first night.
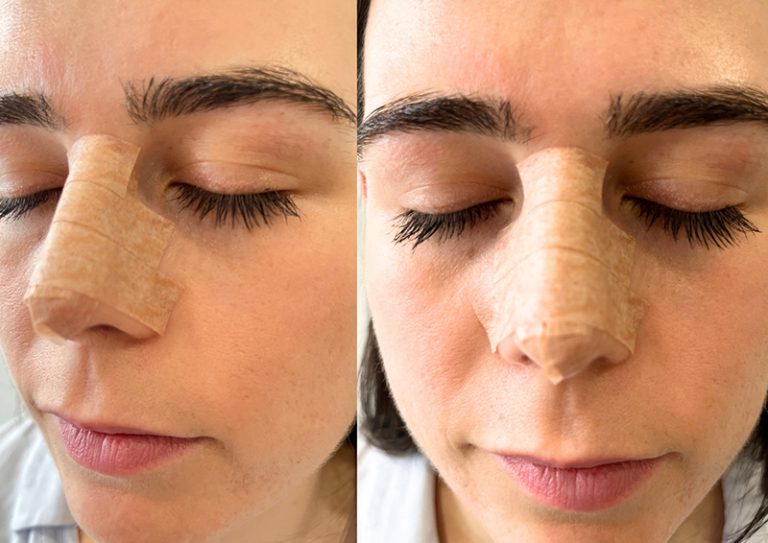
At the end of the operation a small external splint is applied to protect the nasal bones, and soft internal splints may be placed if septal work has been done. A drip pad under the nose absorbs light bleeding for the first few days. Written aftercare instructions are provided, a nurse phones you on the second day, and you are reviewed at one week for splint removal, again at two to three weeks, and then at intervals through the first year as the nose settles.
Aftercare
Recovery after rhinoplasty
Recovery after rhinoplasty varies from one person to another. The experience depends on the type of surgery performed, the extent of structural work involved, individual healing patterns, and whether functional concerns are also being addressed.
Early recovery
For most patients, the most noticeable swelling and bruising occur in the first one to two weeks after surgery.
Activity and exercise
Light daily activity is often resumed first. Heavier exercise and activities with a risk of nasal impact may need to wait longer.
Longer-term healing
Swelling changes over time. Early swelling usually improves first, while more subtle swelling, particularly through the tip, may take longer to settle. In many patients, refinement continues over 12 to 18 months, and sometimes longer.
Recovery, limitations, aftercare, and review appointments are discussed as part of the consultation.
Combining procedures
Combining rhinoplasty with other procedures
Rhinoplasty is often combined with septoplasty when a deviated septum contributes to both the appearance of the nose and nasal obstruction. Performing both in one operation, known as septorhinoplasty, also allows septal cartilage to be used for structural grafts where needed. Learn more about septoplasty.
Because the nose is judged in relation to the whole face, profile balance is assessed at consultation. In selected patients, facial fat transfer may be discussed alongside rhinoplasty to address volume loss in the cheeks or chin region. Patients with a history of cleft lip are assessed for cleft rhinoplasty, which addresses the particular asymmetries of the cleft nose.
Combining procedures means one anaesthetic and one recovery period, but it lengthens the operation and may involve an overnight stay. Whether combining is appropriate depends on your anatomy, goals and health, and is discussed individually.
Rhinoplasty Before and After Photos
Each case below shows one patient of Dr Rodrigo Teixeira photographed before surgery and after healing, from the profile, oblique and front views, taken with the same lighting and angles. Results vary between individuals, and these photographs do not predict your outcome. All surgery carries risks, which are discussed at consultation. Published with each patient’s consent.
Case 1 — Rhinoplasty and septoplasty
Photographs before surgery and six months after surgery. Please note that it may take 12 months or longer for final results, and swelling to completely subside.



Case 2 — Primary rhinoplasty and septoplasty
Photographs before surgery and six months after surgery. Please note that it may take 12 months or longer for final results, and swelling to completely subside.


Case 3 — Rhinoplasty, septoplasty and turbinoplasty
Surgery to treat nasal obstruction and change the shape of the nose, using a structural open rhinoplasty approach.


Case 4 — Rhinoplasty, septoplasty and turbinoplasty
Surgery for nasal obstruction, deviated septum and hypertrophic turbinates. Rhinoplasty was performed to improve both function and aesthetics.


Our Clinic in Ivanhoe East, Melbourne
Unveil Aesthetics and Plastic Surgery is located in Ivanhoe East, around 10 kilometres from Melbourne’s CBD. The clinic on Lower Heidelberg Road is accessible by car, with parking nearby.
When you arrive, our reception team will assist with check-in and appointment coordination. Care is centred on clear communication, clinical professionalism, and structured follow-up throughout the consultation, surgical planning, and recovery process.
Questions
FAQs about Rhinoplasty
Suitability depends on the nature of your concern, your nasal anatomy and structural support, skin thickness, general health and whether your expectations align with what surgery can realistically achieve. Rhinoplasty is generally considered once nasal growth is complete, from the late teens onward. Previous nasal filler, injury or surgery is taken into account. A consultation with Dr Teixeira is required to assess suitability properly.
In some cases, yes. Breathing difficulty may relate to a deviated septum, narrowing of the internal or external nasal valves, weak cartilage support or changes after injury. These are assessed as part of rhinoplasty planning, and functional work such as septoplasty, spreader grafts or other structural support may be included in the same operation where appropriate. Not all breathing concerns are surgical, so assessment comes first.
Rhinoplasty is surgery that changes the shape, structure and, where needed, the function of the nose. Septoplasty specifically straightens or repositions the septum, the wall of cartilage and bone dividing the nasal passages, to improve airflow. The two are often performed together as a septorhinoplasty when a patient has both cosmetic and breathing concerns. Septoplasty alone does not change the outward appearance of the nose.
The first consultation covers what concerns you, examination of the nose inside and out, assessment of breathing, skin thickness, tip support and how the nose sits with the rest of your face, and a review of your medical and treatment history. Clinical photographs are taken and imaging may be used to support discussion. You then discuss what may be achievable, the likely surgical approach, limitations, risks, recovery and fees, and whether surgery is the right option for you.
Recovery varies with the extent of surgery and individual healing. The external splint is usually removed at one week, and most bruising and obvious swelling settles over two to three weeks. Strenuous exercise is avoided for about four weeks and contact sports for six weeks. Glasses should not rest on the nose for four weeks after the splint comes off. Subtle swelling, particularly at the tip, continues to refine over twelve months or longer.
Revision rhinoplasty may be considered when a previous nose operation has left cosmetic, structural or breathing concerns, such as a persistent hump, tip irregularity, collapse of the nasal sidewalls or a blocked airway. Because scar tissue and altered anatomy make these operations more complex, revision is usually not planned until healing from the first surgery is complete, generally after twelve months. Cartilage grafts from the septum, ear or rib may be needed.
The total cost has several components: the surgeon’s fee, the anaesthetist’s fee, the hospital fee and follow-up care. It depends on the complexity of the surgery, whether functional work such as septoplasty is included, whether grafts are needed and whether it is a primary or revision procedure. Purely cosmetic rhinoplasty does not attract a Medicare rebate or health fund cover; some functional procedures may, if criteria are met. A written, itemised quote is provided after consultation.
Rhinoplasty is performed under general anaesthetic in an accredited private hospital, with a specialist anaesthetist. Surgery usually takes two to four hours depending on the structural work involved. Whether you go home the same day or stay one night depends on the extent of surgery, whether it is combined with another procedure and what is most comfortable for you; this is decided with you during planning.
Yes. A small external splint protects the nose for about a week and is removed at your first review. Depending on the surgery, soft internal splints may also be placed and are removed at one to two weeks. Expect a drip pad under the nose for a few days, and avoid blowing your nose for two weeks and flying for at least one week. Written aftercare instructions are provided before you go home.
Journal
Rhinoplasty Surgery Blog
Revision Rhinoplasty: Timing, Healing and Readiness
Rhinoplasty Recovery: Swelling & Results Explained